Surgical Robotics
From da Vinci to Hugo and OTTAVA, authorized one indication at a time.
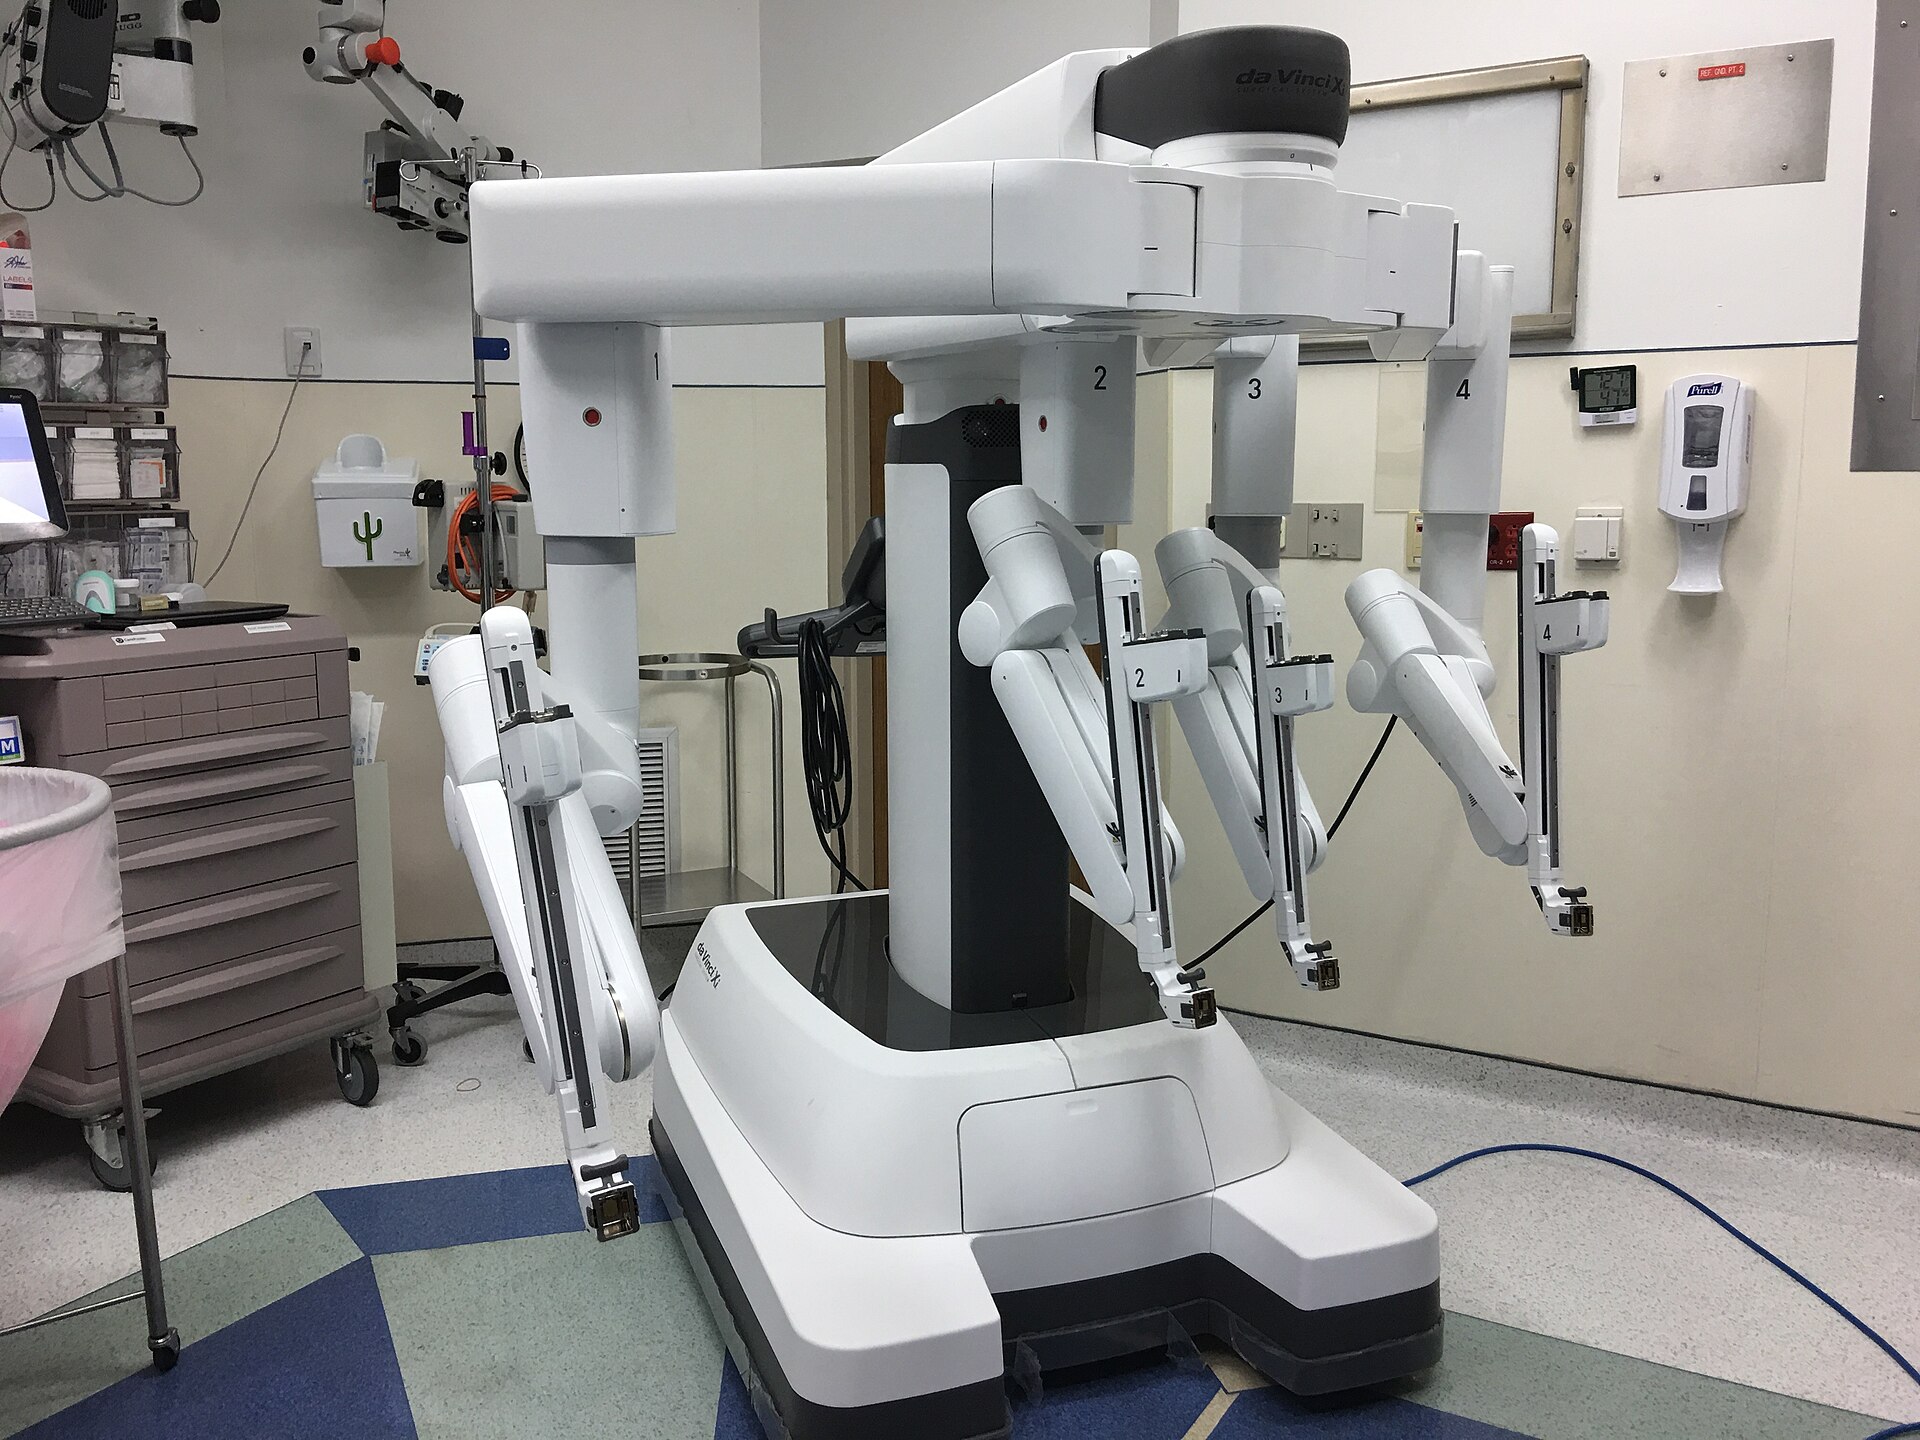
Surgical robotics is the use of robots to position or move surgical instruments, today mostly teleoperated systems for minimally invasive surgery that scale and filter a surgeon's hand motion. Intuitive had 11,710 da Vinci systems installed by June 30, 2026Source 11, and most commercial platforms sit at level 0, with no decision autonomySource 12.
The teleoperation baseline
A da Vinci surgeon sits at a console away from the table and moves hand controllers, while patient-side arms carry wristed instruments and an endoscope. The robot adds motion scaling, tremor filtering and wrists that articulate inside the body. Yang and colleagues place such a system at Level 0, no autonomy, because even with motion scaling its output represents the surgeon's desired motionSource 1. At level 1 a robot gives cognitive and physical assistance, and at level 2 it performs a surgical task autonomouslySource 12.

Motion scaling
The robot shrinks the surgeon's hand motion, wobble and all
3 to 1
Drag on the right-hand plate to move the stylus3 to 1 · 30 mm at the hand, 10 mm at the tip
Illustrative: an authored stroke and scale settings; the division is exact
How this was made
Motion scaling is one of the things a teleoperated surgical robot adds to the surgeon's hand: the console divides each hand movement before it reaches the instrument, so a large, comfortable movement becomes a fine one inside the patient, and any wobble in the hand is divided too. Yang and colleagues count it as Level 0, no autonomy, because the instrument still follows the surgeon's own motion.
The drawing is a reducing pantograph doing the same thing with four bars. With the stylus at H and the fixed pivot at O, the tip sits on the line between them at 1/scale of the way out, so tip = hand ÷ scale for every point of the stroke. The two knurled scale pins move along the bars' hole rows to set 2 to 1 up to 5 to 1; the pips beside each hole count the scale it sets.
Illustrative: the 30 mm stroke and its wobble of 1.5 mm either side are authored, and so are the scale settings; a real system also filters tremor, which this pantograph only divides. The millimetre rules on both plates are the same scale, so the two traces can be compared directly.
Motion scaling as Level 0 autonomy: Yang et al., Science Robotics (2017).
The field began with positioning. In 1988 Kwoh and colleagues reported a robot with improved absolute positioning accuracy for CT-guided stereotactic brain surgerySource 13. Marescaux and colleagues reported transatlantic robot-assisted telesurgery in 2001Source 14. Intuitive says cardiac surgery was the first specialty cleared on the original da Vinci, in 2002Source 15.
Da Vinci 5, cleared in March 2024, has more than 150 enhancements over Xi and more than 10,000 times its computing powerSource 3. Its optional Force Feedback instruments let the surgeon feel forces at the instrument tips, and Intuitive reported up to 43 percent less force on tissue in preclinical trialsSource 3. In a preclinical study by 28 surgeons, the feature at its high setting cut maximal force by 36, 41 and 55 percent in retraction, dissection and suturingSource 16.
Logs from 444 thoracic procedures by 73 surgeons show median tip force falling from 1.79 N with feedback off to 1.32 N at the high settingSource 17. A pilot study of 68 colorectal operations found less applied force without a significant change in bowel function or length of staySource 18. In January 2026 the FDA cleared da Vinci 5 for selected cardiac procedures using instruments without force feedbackSource 15.
Intuitive reports that its installed base grew 12 percent in 2025 to 11,106 systems, and that da Vinci procedures grew roughly 18 percent worldwide in 2025Source 4. Of 532 fourth-quarter placements, 303 were da Vinci 5sSource 4. In the second quarter of 2026, procedures grew about 15 percent and 246 of 468 placements were da Vinci 5sSource 11.
| System | Design focus | Differentiator | Regulatory path |
|---|---|---|---|
| Intuitive da VinciL0 | Multiport and single-port teleoperated soft-tissue surgery; the incumbent platform | da Vinci 5 ships 150+ enhancements over Xi, including Force Feedback instruments and 10,000x the computing power | da Vinci 5 via 510(k) in March 2024, cleared for selected cardiac procedures in January 2026; 11,710 systems installed by June 30, 2026Level 0: every motion is the surgeon’s command, scaled and tremor-filtered |
| CMR VersiusL0 | Compact, modular multiport system that moves between operating rooms and care settings | Biomimetic arm design with small fully wristed instruments and an open console; Versius Plus adds near-infrared imaging, new instruments and updated software | US entry via FDA De Novo (October 2024) for adult cholecystectomy; Versius Plus 510(k) December 2025Level 0: teleoperated, with the surgeon at an open console rather than enclosed |
| Medtronic HugoL0 | Modular multiport robotic-assisted surgery system, cleared in the US for urology | Already used in more than 30 countries before its US clearance | US 510(k) clearance on December 3, 2025 for urologic procedures including prostatectomy, nephrectomy and cystectomyLevel 0: teleoperated from a surgeon console |
| J&J OTTAVAL0 | Table-integrated soft-tissue robot for general surgery | J&J says it occupies 30 to 50 percent less space than boom- and cart-mounted systems | FDA De Novo authorization in July 2026 for general-surgery procedures including gastric bypass, cholecystectomy and hiatal hernia repairLevel 0: teleoperated from a surgeon console |
| Moon Surgical MaestroL1 | Two-armed hold-and-position assistant for standard laparoscopic surgery | Works with standard laparoscopic cameras and instruments; ScoPilot adds AI camera-following of the instrument tip (March 2025) | First 510(k) December 2022; commercial system cleared June 2024Level 1: robot assistance; ScoPilot automates camera positioning on demand while the surgeon keeps continuous control |
Every system in the table is Level 0 or Level 1 on the Yang scaleSource 1.
The challengers and what they compete on
CMR Surgical's Versius is a modular multiport system whose arms are separate bedside units that can move between operating rooms, driven from an open consoleSource 5. In October 2024 the FDA authorized it through De Novo for adult cholecystectomy, the first multiport soft-tissue general surgical system authorized that waySource 5. CMR put robot-assisted surgery at about 2.5 percent of nearly 10 million annual US major operating-room proceduresSource 5. Versius Plus was cleared in December 2025, and by March 2026 CMR reported more than 45,000 Versius patients in more than 30 countriesSource 6 Source 19.
Medtronic's Hugo was cleared on December 3, 2025 for urologic procedures including prostatectomy, nephrectomy and cystectomySource 20. Medtronic says it had already been used in more than 30 countriesSource 20. Its first US case followed at Cleveland Clinic in February 2026Source 21.
Medtronic says about 80 percent of US abdominal urologic surgery is already robot-assistedSource 21. In June 2026 it filed 510(k)s for general and gynecologic surgerySource 22.
Johnson & Johnson's OTTAVA, a table-integrated soft-tissue robot, received De Novo authorization in July 2026 for general-surgery procedures including gastric bypass, cholecystectomy and hiatal hernia repairSource 23. J&J says it occupies 30 to 50 percent less space than boom- and cart-mounted systemsSource 23. In a Michigan registry of 169,404 patients, robotic use in common general-surgery procedures rose from 1.8 percent in 2012 to 15.1 percent in 2018Source 24.
Moon Surgical's Maestro is a two-armed assistant that holds and positions the laparoscopic camera and instruments, using the cameras and graspers a hospital already owns. Its first 510(k), in December 2022, rested on substantial equivalence to a 1990s endoscope positionerSource 7. A single surgeon used it without an assistant in a 30-patient seriesSource 7.
The commercial system was cleared in June 2024Source 8. ScoPilot, cleared in March 2025, runs on NVIDIA Holoscan on the robot and lets the laparoscope follow the instrument tip on demandSource 9, Level 1 assistance on the Yang scaleSource 1.
Camera following
At Level 1 the robot takes over only the camera
Camera
Drag on the board to move the right instrumentFollows the tip · tip in view · Level 1
Schematic: an illustrative trainer and drill
How this was made
Yang and colleagues place a robot that assists under the surgeon's continuous control at Level 1, one step above a teleoperated system that only follows the surgeon's hands. Moon Surgical's ScoPilot, cleared in March 2025, is such a step: on demand, the laparoscope held by its Maestro arm follows a chosen instrument tip, and the surgeon steers the view without letting go of the instruments.
The drawing is a box trainer on a bench. Two instruments, the surgeon's hands, enter through ports in the soft pad over the peg board, and a laparoscope enters through a third, clamped to a two-link robot arm on a column. The pale pool on the board, lit, is what the scope sees. Every port is a fixed pivot, so each outside end swings opposite its tip. With following on, the arm turns the scope about its port to keep the pool on the right instrument's tip; with it off, the scope stays where it was put, and the tip can leave the picture.
Schematic: the trainer, the drill and the arm are illustrative, and no number is claimed. How ScoPilot finds the tip is not drawn; the arm here simply aims the scope at it.
Camera following: Moon Surgical's ScoPilot clearance (2025). Level 1 assistance: Yang et al., Science Robotics (2017).
The precision and reliability bar
A policy that succeeds 95 percent of the time per step compounds to 21.5 percent over 30 steps, the arithmetic of the reliability gap. FDA reports on robotic surgery from 2000 to 2013 included 144 deaths (1.4 percent of 10,624 reports), 1,391 patient injuries and 8,061 device malfunctionsSource 25. At clearance, Intuitive said da Vinci 5 would first go to a small number of US customers to gather data on real useSource 3. In the ROLARR trial of 471 rectal-cancer patients, robotic assistance did not significantly reduce conversion to open surgery: 8.1 percent against 12.2 percent for conventional laparoscopy (P = .16)Source 26.
In 2016 STAR, the Smart Tissue Autonomous Robot, performed supervised autonomous soft-tissue anastomosis in vivo in pigsSource 2. Its suture spacing and leak pressure matched or exceeded both expert surgeons and robot-assisted techniqueSource 2. In 2022 a robot performed laparoscopic small-bowel anastomosis in pigs over a one-week survival period, with the operator choosing among autonomously generated plansSource 27. It outperformed expert manual and robot-assisted technique on consistency and accuracySource 27.
In 2025 SRT-H, whose high-level language policy guides a low-level policy through long-horizon steps and helps it recover from errors, ran ex vivo cholecystectomy experimentsSource 28. It succeeded on all eight gallbladders tested without human interventionSource 28. Hierarchical policies covers that design.
A device is authorized for an indication, a named procedure in a named population, and expansion needs a new clearance. Yang and colleagues argue that a highly autonomous robot starts practicing medicine, which in the US falls to medical societiesSource 1. They propose licensing robotic surgeons through the medical establishment, as is done for human surgeonsSource 1.
Yang and colleagues put the gap between the 510(k) and premarket-approval pathways at tens of millions of dollars and years of review, and add that risk tolerance to autonomous robots is expected to change as autonomous machines such as self-driving cars become commonplaceSource 1. Haidegger names the lack of autonomy benchmarks and standards as a major barrier to commercialising autonomous surgical robotsSource 29, and safety and assurance covers the general case.
What robot learning takes from it
Clinical recordings could become training data. SRT showed that imitation learning works on the da Vinci despite its approximate kinematics, using a relative action formulation, so the large repository of clinical data may be used for robot learning without further correctionsSource 30. Open-H-Embodiment pools synchronized video and kinematics from more than 50 institutions and platforms including Versius, da Vinci, the da Vinci Research Kit and MaestroSource 31.
Its GR00T-H model was the only one evaluated to finish a structured suturing benchmark end to end, in 25 percent of trials against 0 percent for all othersSource 31. It reached a 64 percent average success rate across a 29-step ex vivo suturing sequenceSource 31. Major datasets lists its general-robotics peers.
In September 2026, Shutong Jin, Ken Goldberg and colleagues reported AGRO-SUVIDE, a coding-agent framework that builds debridement skills from one expert demonstration and retries a skill when its checks fail. In 340 physical trials on the da Vinci Research Kit, it removed single fragments from a viscoelastic substrate with 85% average success and completed three consecutive removals 60% of the time, or 95% with one human interventionSource 10.
Intuitive says da Vinci 5's Force Feedback measurements add a new data stream to surgical data scienceSource 3, and Moon Surgical frames Maestro's sensing and onboard compute as the substrate for next-generation physical AISource 9. A 2022 review found surgical data science still lacking translational success stories, and its roadmap covers data acquisition under regulatory constraints, annotation and sharingSource 32. The same question of how much evidence earns autonomy runs through autonomous vehicles, drones and space robotics.
See also
- Hierarchical Approaches
From SayCan and Code as Policies to the hierarchies in Helix and pi0.5.
- Major Datasets
The major open robot datasets and what each collected.
- Safety and Assurance
What ships is a verifiable safety layer around the learned policy.
Linked from
- Safety and Assurance
What ships is a verifiable safety layer around the learned policy.
- Drones and Aerial Robotics
Autonomous flight, from state estimation to champion-level racing.
- Space Robotics
Robots where repair is impossible, from Mars to orbit.
References
Guang-Zhong Yang, James Cambias, Kevin Cleary, Eric Daimler, James Drake, Pierre E. Dupont, and 6 more, Science Robotics 2(4), eaam8638, 2017.
https://doi.org/10.1126/scirobotics.aam8638
Azad Shademan, Ryan S. Decker, Justin D. Opfermann, Simon Leonard, Axel Krieger, Peter C. W. Kim, Science Translational Medicine 8(337), 337ra64, 2016.
https://doi.org/10.1126/scitranslmed.aad9398
Intuitive Surgical, GlobeNewswire, 14 March 2024.
https://www.globenewswire.com/news-release/2024/03/14/2846718/7637/en/Intuitive-Announces-FDA-Clearance-of-Fifth-Generation-Robotic-System-da-Vinci-5.html
Intuitive Surgical, GlobeNewswire, 22 January 2026.
https://www.globenewswire.com/news-release/2026/01/22/3224266/0/en/intuitive-announces-fourth-quarter-earnings.html
U.S. Food and Drug Administration, FDA 510(k) Premarket Notification Database, 2025.
https://www.accessdata.fda.gov/cdrh_docs/pdf25/K252111.pdf
Ruben D. Salas Parra, David Pechman, SAGES Technology and Value Assessment Committee, 2023.
https://www.sages.org/publications/tavac/moon-surgical-maestro-surgical-robotics-system
U.S. Food and Drug Administration, FDA 510(k) Premarket Notification Database, 2024.
https://www.accessdata.fda.gov/cdrh_docs/pdf24/K240598.pdf
Moon Surgical, PR Newswire, 18 March 2025.
https://www.prnewswire.com/news-releases/moon-surgical-receives-fda-clearance-for-scopilot-on-maestro-industrys-first-ai-enhanced-intraoperative-capability-powered-by--nvidia-holoscan-302404920.html
Shutong Jin, Ziyang Chen, Preethi Satish, Meadow Shen, Gary Guthart, Florian T. Pokorny, and 1 more, 2026.
https://arxiv.org/abs/2609.34823
Intuitive Surgical, GlobeNewswire, 2026-07-16.
https://www.globenewswire.com/news-release/2026/07/16/3328793/0/en/intuitive-announces-second-quarter-earnings.html
Aleks Attanasio, Bruno Scaglioni, Elena De Momi, Paolo Fiorini, Pietro Valdastri, Annual Review of Control, Robotics, and Autonomous Systems 4:651-679, 2021.
https://doi.org/10.1146/annurev-control-062420-090543
Y. S. Kwoh, J. Hou, E. A. Jonckheere, S. Hayati, IEEE Transactions on Biomedical Engineering 35(2):153-160, 1988.
https://doi.org/10.1109/10.1354
Jacques Marescaux, Joel Leroy, Michel Gagner, Francesco Rubino, Didier Mutter, Michel Vix, and 2 more, Nature 413(6854):379-380, 2001.
https://doi.org/10.1038/35096636
Intuitive Surgical, GlobeNewswire, 2026-01-26.
https://www.globenewswire.com/news-release/2026/01/26/3225716/7637/en/Da-Vinci-5-Cleared-for-Cardiac-Procedures.html
Michael M. Awad, Mathew C. Raynor, Mika Padmanabhan-Kabana, Lana Y. Schumacher, Jeffrey A. Blatnik, Surgical Endoscopy 38(10):6193-6202, 2024.
https://doi.org/10.1007/s00464-024-11131-z
Peter J. Kneuertz, Robert Mostellar, Robert E. Merritt, Elliot L. Servais, Brian Mitzman, Nestor R. Villamizar, and 5 more, Journal of Robotic Surgery 19:632, 2025.
https://doi.org/10.1007/s11701-025-02781-9
Grace C. Chang, Upinder Sidhu, Debra Lai, Gabriela Vargas, Sai Shah, Laila Rashidi, The American Journal of Surgery 248:116518, 2025.
https://doi.org/10.1016/j.amjsurg.2025.116518
CMR Surgical, GlobeNewswire, 2026-03-26.
https://www.globenewswire.com/news-release/2026/03/26/3262907/0/en/cmr-surgical-announces-45-000-patients-treated-globally-as-robotic-assisted-surgery-company-makes-its-u-s-debut.html
Medtronic, Medtronic Newsroom, 2025-12-03.
https://news.medtronic.com/2025-12-03-Medtronic-announces-FDA-clearance-of-Hugo-TM-robotic-assisted-surgery-system-for-urologic-surgical-procedures
Medtronic, Medtronic Newsroom, 2026-02-17.
https://news.medtronic.com/2026-02-17-Medtronic-announces-first-surgery-with-Hugo-TM-robotic-assisted-surgery-system-in-the-U-S-performed-at-Cleveland-Clinic
Medtronic, Medtronic Newsroom, 2026-06-03.
https://news.medtronic.com/2026-06-03-Medtronic-submits-510-k-filings-to-expand-Hugo-TM-robotic-assisted-surgery-system-into-general-and-gynecologic-specialties-in-the-United-States
Johnson & Johnson, Johnson & Johnson press release, 2026-07-22.
https://www.jnj.com/media-center/press-releases/johnson-johnson-receives-fda-market-authorization-in-the-u-s-for-its-ottava-robotic-surgical-system
Kyle H. Sheetz, Jake Claflin, Justin B. Dimick, JAMA Network Open 3(1):e1918911, 2020.
https://doi.org/10.1001/jamanetworkopen.2019.18911
Homa Alemzadeh, Jaishankar Raman, Nancy Leveson, Zbigniew Kalbarczyk, Ravishankar K. Iyer, PLOS ONE 11(4):e0151470, 2016.
https://doi.org/10.1371/journal.pone.0151470
David Jayne, Alessio Pigazzi, Helen Marshall, Julie Croft, Neil Corrigan, Joanne Copeland, and 10 more, JAMA 318(16):1569-1580, 2017.
https://doi.org/10.1001/jama.2017.7219
H. Saeidi, J. D. Opfermann, M. Kam, S. Wei, S. Leonard, M. H. Hsieh, and 2 more, Science Robotics 7(62):eabj2908, 2022.
https://doi.org/10.1126/scirobotics.abj2908
Ji Woong Kim, Juo-Tung Chen, Pascal Hansen, Lucy Xiaoyang Shi, Antony Goldenberg, Samuel Schmidgall, and 8 more, Science Robotics 10(104):eadt5254, 2025.
https://doi.org/10.1126/scirobotics.adt5254
Tamás Haidegger, IEEE Transactions on Medical Robotics and Bionics 1(2):65-76, 2019.
https://doi.org/10.1109/TMRB.2019.2913282
Ji Woong Kim, Tony Z. Zhao, Samuel Schmidgall, Anton Deguet, Marin Kobilarov, Chelsea Finn, and 1 more, 2024.
https://arxiv.org/abs/2407.12998
Open-H-Embodiment Consortium, Nigel Nelson, Juo-Tung Chen, Jesse Haworth, Xinhao Chen, Lukas Zbinden, and 209 more, 2026.
https://arxiv.org/abs/2604.21017
Lena Maier-Hein, Matthias Eisenmann, Duygu Sarikaya, Keno März, Toby Collins, Anand Malpani, and 45 more, Medical Image Analysis 76:102306, 2022.
https://doi.org/10.1016/j.media.2021.102306
Spot a factual error or missing qualification? Report a content correction.